Why weight-loss maintenance is so demanding
Weight-loss maintenance is so challenging because it requires us to develop an entirely new lifestyle and sense of who we are to move away from the behaviours and lifestyle that led to us gaining weight in the first place.
An analogy we like to share with our members is that of forging new footpaths in a dense forest.
Imagine a woodland that you walk through every day, where the trails are clearly marked, easy to follow, and you can walk through them without thinking, because you know the paths so well.
Then, imagine you see a gap in the trees where a new path to an area you’ve not discovered before would be possible, but you need to first forge this new path by moving fallen branches, cutting down grass, and repeatedly walking on the path each day consistently for a long time, before the ground becomes thinner and the path becomes clearer.
Each day you return to your newer path, and it’s hard work; you have to keep forging your way through the bush for the path to become easier.
But sometimes it gets harder; storms blow new branches in your way, and spring encourages fresh growth of weeds and nettles that keep encroaching on the path.
All the while, our old paths are still there. If we wanted to, we could return to them without any thought.
We wouldn’t have to put in any real effort to clear them; we would just follow, much like we always have. This is the challenge of weight-loss maintenance, and of any meaningful behaviour-change process.
Each day we have to return to the new path and once again put in more effort to clear the way forward. There are always new obstacles and challenges to overcome before the path becomes clear.
It’s within the obstacles of this challenge that most of us get stuck. Weight loss, in the early stages, can feel easy. We feel motivated, excited even, and we notice improvements quickly.
However, at the first sign of difficulty or evidence that we’re no longer making progress (because the scales don’t go down one day, for example), we convince ourselves that what we’re doing is no longer working, and we give up.
Life is already challenging for many of us. Social pressures, financial stress, work, and our health can all place an impossible burden on our wellbeing. It can be extremely overwhelming.
It’s no surprise, then, when we’re already balancing so many responsibilities, that maintaining weight loss over the long term is so challenging. This isn’t just what we’ve observed in practice, supporting over 300,000 members over the past 10 years; it’s also clear in the evidence on weight-loss maintenance.
A review by Greaves and colleagues brought together 26 studies involving 710 people who described their experiences of weight-loss maintenance.3
Participants described an ongoing conflict between the changes needed to maintain their weight and established habits, social situations, and emotional needs.
Developing new eating habits and lifestyle changes was particularly demanding when it meant giving up things they enjoyed or relied on to manage difficult feelings.3
For example, if we’d used food to cope with challenging emotions in the past, then finding other ways to manage our feelings and emotions when we’re already feeling overwhelmed from everyday life is extremely difficult.
Similarly, trying to improve our health can bring up a direct challenge to the very sense of who we are.
Maybe we used to always be the one who got the most drunk on a night out and would leave our friends in hysterics with our antics.
While entertaining, maybe that behaviour is no longer serving us and we want to move away from it, but what would our friends think? Would they approve of us being more balanced with our intake? Or would they call us boring for not having fun in the same way anymore?
Still, some people in the review by Greaves and colleagues described finding ways to enjoy social occasions and manage difficult feelings without returning to the behaviours they were trying to change.3
In the example above, that might involve explaining to our friends why we want to drink less, or suggesting that we meet for lunch or a walk instead.
We’re still making time for those relationships while changing how we spend that time together.
Similarly, if food has been our main way of coping with distress, we may need help with the distress itself. That could involve talking to someone we trust or seeking professional support, particularly when anxiety, depression, or past trauma affects our eating.
People in the review also described learning from occasions when things hadn’t gone to plan. They tried to understand what had happened and adjust their approach, rather than deciding that a setback meant they couldn’t manage their weight.3
For example, if we regularly order a takeaway after working late, we could prepare extra portions on another day and freeze them. We’re responding to the circumstances that made cooking difficult, instead of expecting ourselves to have more motivation after another exhausting day.
Some participants also began to enjoy cooking or being active for reasons beyond weight loss. Exercise became something they enjoyed or used to manage stress, and preparing food became something they took pride in.3
For some, this changed how they saw themselves. They began to identify as someone who enjoyed being active or cooking, and the changes felt less like temporary restrictions they were waiting to stop.3
Still, it’s not just our psychology and environment that makes weight-loss maintenance so hard; it’s also our biology and how our brain responds to losing body fat.
What changes in the body after weight loss
When we lose body fat, our brain responds by attempting to regain the fat we’ve lost. This aligns with set point theory, which states that the brain adapts to a certain body fat percentage.
When our body fat levels fall below our set point, the brain can respond by lowering our metabolism (the energy we burn each day) and increasing hunger levels, encouraging us to eat more.
This response to fat loss is an evolutionary requirement to protect us against famine.
Our ancestors were never guaranteed a consistent food supply, so we had to evolve a system to encourage us to hunt and gather as much food as possible to improve our chances of survival and reproduction.
It’s not clear from the evidence we have how much our metabolism can slow in each individual and how long this lasts after we lose weight.1,2
Still, what is clear is that changes do occur in our body’s demands for energy to regain the weight we’ve lost.
In a study by Sumithran and colleagues, 50 adults started a ten-week very-low-energy diet. Among those who completed the study, average weight loss was 13.5 kg.2
A year later, the 34 people included in the follow-up analysis still reported more hunger than before losing weight.2
Leptin levels were also still lower, alongside changes in other appetite-related hormones. Fat cells produce leptin to tell the brain how much fat is stored in the body.2
The study was small and used a restrictive diet, so it can’t predict how everyone will respond to weight loss. But it shows that increased hunger can persist well beyond the period when someone is actively losing weight.2
Researchers also followed 14 contestants from the television show The Biggest Loser for six years. They’d lost an average of 58 kg during the show and regained 41 kg by the follow-up. Despite this regain, their metabolism remained slower than expected.8
At rest, their bodies were using around 500 fewer calories a day than the researchers predicted for their age and the amounts of fat and lean tissue in their bodies.8
That estimate already accounted for changes in lean tissue, including muscle. So, the finding couldn’t simply be explained by losing muscle during weight loss and regaining fat afterwards.8
The researchers suggested this could reflect a continuing biological response to weight loss.
However, the study didn’t measure changes in the brain or establish that it was defending a fixed body-fat percentage.8
These were also 14 people who’d taken part in an extreme diet and exercise programme. We shouldn’t assume that everyone who loses weight will experience the same response.8
A review of 33 studies found mixed results on how much our metabolism slows after weight loss.
Studies with stronger methods generally found little or no reduction beyond what we’d expect from having a smaller body, particularly once people’s weight had stabilised.1
Even in the Biggest Loser study, eight of the 14 participants remained at least 10% below their starting weight six years later, despite their bodies still using less energy at rest than expected.8
Still, maintaining weight loss may require more effort than we’d expect from looking at someone’s eating habits alone.
We might improve our eating habits by eating balanced meals and making time to exercise, yet still feel hungry more often than we did before losing weight.
That hunger doesn’t disappear because we understand nutrition or want to improve our health.
When we’re already managing the pressures of everyday life, repeatedly resisting the urge to eat can make even well-established habits difficult to sustain.
The biological challenges that come with weight loss are why it’s essential to focus on all of the factors that impact our hunger and cravings.
So yes, focus on eating habits to give our bodies what they need, but also understand how our food environment, sleep, stress, habits, and unmet psychological needs can affect our hunger and desire to eat.
Why habits help but aren’t always enough
Healthy habits can reduce the effort involved in maintaining weight loss, but they won’t remove every cause of weight gain.
Some of us will still struggle with hunger, food noise, or emotional eating even when we eat well and exercise regularly.
Our everyday habits form the foundation of our health, but we also need psychological tools and a resilient mindset to maintain them when life gets difficult and we face obstacles along the way.
For example, we might have developed a routine of preparing balanced meals, but still turn to food for comfort after an argument with our partner or an overwhelming day at work.
The meal may have provided the nutrients our body needs, but it hasn’t resolved the argument or reduced the pressure we’re under.
If food has been how we’ve managed those challenging feelings in the past, changing what we cook won’t necessarily change why we want to eat afterwards.
Alongside our eating habits, we need to understand what we’re feeling and find other ways to meet those needs. That might involve talking through a problem with someone we trust, asking for help with responsibilities, or seeking professional support with ongoing distress.
We also need to develop the ability to respond to setbacks without deciding that everything we’ve been doing has failed.
Maybe we miss a week of exercise because work becomes overwhelming. We might then tell ourselves that we never stick to anything, and question whether there’s any point in trying again.
But missing exercise during a demanding week doesn’t mean we’re incapable of maintaining an active lifestyle. It tells us that our usual routine was difficult to manage in those circumstances.
We can use that experience to reconsider what we’re expecting of ourselves. A shorter walk might be manageable during a busy week, even if our usual exercise sessions aren’t. We can adjust what we do without deciding that doing less makes it pointless.
Participants in the Greaves review described learning from setbacks, adapting their plans, and finding other ways to manage difficult emotions. They developed these skills alongside their eating and exercise habits.3
Developing a resilient mindset involves practising these responses, so that a difficult week becomes something we can understand and respond to, rather than a reason to give up.
It also involves recognising when the demands we’re facing exceed what we can manage alone.
Asking for help with persistent hunger, emotional distress, or overwhelming responsibilities may be necessary to maintain healthy habits.
Maintaining weight after Mounjaro or Wegovy
Another tool that has become available in recent years is the use of GLP-1 medications to support weight loss and weight maintenance.
Mounjaro and Wegovy can reduce hunger and food noise, making changes to our eating habits easier to manage.
However, feeling less hungry while taking medication doesn’t necessarily mean that the reasons we struggled with our weight before treatment have gone away.
For example, we might find it easier to eat less, but still rely on food to manage difficult emotions.
If hunger and cravings return after stopping medication, we may find ourselves struggling with the same difficulties again. This is why we recommend developing healthy eating habits and practising psychological skills during treatment.
Understanding why we turn to food, and finding other ways to meet those needs, remains important whether we continue medication or eventually stop.
Still, these changes won’t guarantee that maintaining weight without medication becomes manageable for everyone. The studies following people after treatment stops show how difficult this can be.
Among participants followed in the STEP 1 extension, those taking Wegovy had lost an average of 17.3% of their starting weight.
Over the year after stopping, they regained about two-thirds of the weight they’d lost.4
Lifestyle support also ended when Wegovy stopped, so we can’t separate the effects of stopping medication from those of withdrawing support.4
In SURMOUNT-4, diet and activity counselling continued after participants either stayed on Mounjaro or switched to placebo.5
Those switched to placebo gained an average of 14.0% of their weight at the time of switching over the following year. Those continuing Mounjaro lost a further 5.5%.5
However, the trial didn’t test intensive behavioural therapy. It doesn’t tell us whether more personalised support with emotional eating, established habits, and the pressures of everyday life would have reduced weight regain.5
Advice about what to eat and how much to exercise doesn’t necessarily help someone understand why they turn to food when they’re overwhelmed, or how to respond differently.
We therefore shouldn’t assume that everyone will have the same experience after stopping medication.
Some of us may maintain weight loss without it, while others may still need ongoing treatment despite making changes to how we eat and live.
Lower-dose Mounjaro maintenance
A lower maintenance dose of Mounjaro can help some people maintain the majority of the weight they’ve lost, although some weight may return.6
In SURMOUNT-MAINTAIN, 378 participants were randomly assigned to continue taking 10 mg or 15 mg, reduce to 5 mg, or switch to placebo after an initial 60 weeks of treatment.6
Over the following year, the researchers estimated how much of their previous weight loss each group maintained.6
| Treatment during maintenance |
Previous weight loss maintained |
What the estimate means |
| Continue 10 mg or 15 mg |
102.4% |
All the previous weight loss was maintained on average, with a small further reduction |
| Reduce to 5 mg |
71.7% |
Most of the previous weight loss was maintained on average, although some weight returned |
| Switch to placebo |
44.6% |
More than half of the previous weight loss was regained on average |
These percentages describe the amount of weight loss maintained, not how many people maintained their weight.6
From 24 weeks into maintenance, people who’d regained at least half the weight they’d lost could restart Mounjaro if they were taking placebo, or increase their dose if they were taking 5 mg.6
By the end of the study, 67% of the placebo group had restarted Mounjaro, and around 25% of the 5 mg group had increased their dose because of weight regain.6
For people who restarted Mounjaro or increased their dose because of weight regain, the researchers used their highest weight recorded during maintenance before that change. They excluded any later weight changes from these estimates.6
This exclusion means that weight lost after restarting Mounjaro wasn’t counted as weight maintained without medication.6
Measurements taken after someone stopped their assigned maintenance treatment were also excluded.
The table therefore shows statistical estimates, rather than a simple average of everyone’s weight at the end of the study.6
All groups continued receiving diet and activity counselling, but starting intensive behavioural therapy during maintenance was restricted.6
So, the study supports using lower doses of Mounjaro for weight maintenance, but it doesn’t show what would happen with more intensive support to address the psychological and practical difficulties of changing our habits.
Eli Lilly, which manufactures Mounjaro, funded the trial and was involved in its design and analysis.6
At Second Nature, we offer a lower-maintenance dose as one option to maintain weight loss in the long term.
Any change in your GLP-1 medication dose should be agreed with the prescriber, considering hunger, weight changes, side effects, health, and personal preferences.
This trial didn’t test whether gradually reducing the dose until stopping would prevent weight regain.6
Whether we’re on medication or not, our eating habits, physical activity, sleep, and psychological wellbeing are still crucial for our overall health and ability to maintain weight loss in the future.
Medication may make hunger easier to manage, but we also need ways to manage the circumstances and emotions that led to weight gain in the first place.
Our guide on coming off weight-loss injections explores how to come off weight-loss medications without regaining weight in more detail.
What supports long-term maintenance
We recommend eating a diet based on whole foods, finding physical activity we enjoy, and reviewing our hunger, eating habits, sleep, and stress when maintaining weight becomes more difficult.
An approach that leaves us hungry, prevents us from enjoying meals with other people, or requires more time than we have will be difficult to maintain, even if it helped us lose weight initially.
Make balanced meals part of everyday life
We recommend eating a diet based on whole foods, that contains enough protein, fibre, fat, and complex carbohydrates, and limits ultra-processed foods.
But eating well to lose weight and keep it off isn’t about eating as little as possible.
We still need enough food to meet our body’s daily nutritional needs, including enough protein to help maintain muscle mass.
For example, a small salad might contain plenty of vegetables and fibre, but very little protein, fat, or carbohydrate. Adding chicken or tofu provides protein, while brown rice and extra virgin olive oil provide carbohydrate and fat alongside the vegetables.
We can use the balanced plate as a guide: half vegetables, a quarter protein, a quarter complex carbohydrates, and a serving of fat. A palm-sized portion of protein at each meal is a practical starting point.
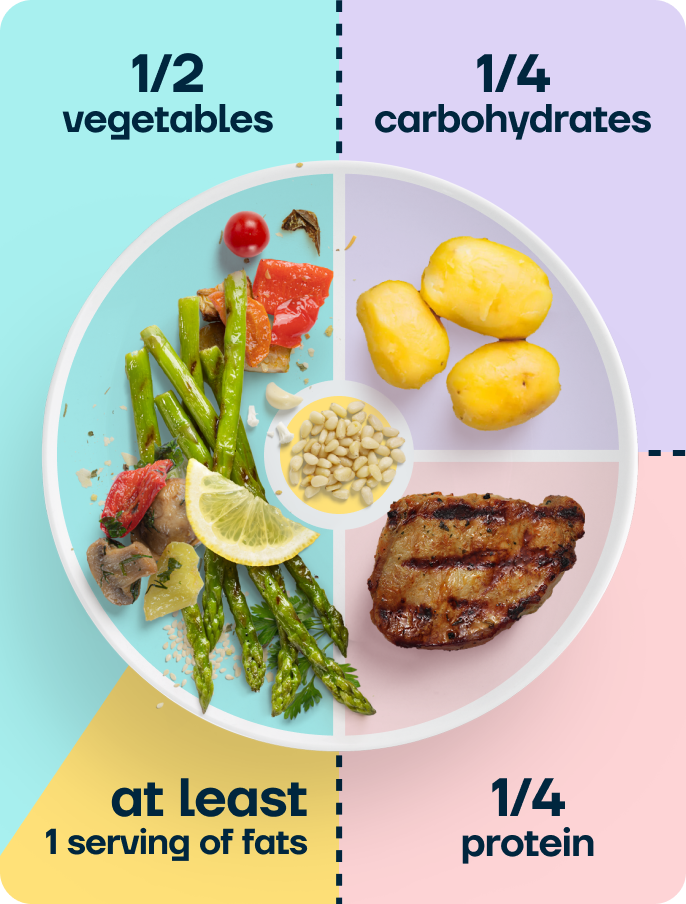
If we’re cooking one meal for ourselves and another for our family every evening, the extra work may be hard to keep up with.
We could adapt a meal everyone already enjoys instead. For example, a tomato-based pasta dish could include lentils or mince for protein, with vegetables served alongside it, so we’re not preparing two separate dinners.
If we dislike the food we’re eating, we need to find meals we prefer, rather than expect ourselves to tolerate a diet we’re already looking forward to stopping.
Find reasons to be active beyond weight loss
We recommend choosing activities that give us something we value beyond weight loss, such as getting stronger, spending time with friends, or having a break from work.
During maintenance, we won’t be motivated to exercise just to lose weight.
If weight loss was our only reason to exercise, we might start to question why we’re making the effort when our weight no longer changes.
But a walk with a friend can give us time to talk, while swimming might give us a break from work or caring responsibilities.
Strength exercises help us maintain muscle and the strength needed for everyday activities, such as carrying shopping or getting up from a chair. They can involve weights, resistance bands, or our own body weight.
Some people in the Greaves review described being motivated by the enjoyment and satisfaction they found in being active, rather than depending only on weight loss to stay interested.3
We may need to try different activities before finding something we want to repeat.
Disliking the gym doesn’t mean we can’t enjoy being active, particularly if a class, a walking group, or exercising at home suits us better.
Notice changes and understand what’s behind them
If our weight is gradually increasing or we’re eating differently, we recommend reviewing what’s changed before deciding we need a stricter diet.
People in the Greaves review described using changes in their weight or how their clothes fit as a prompt to review their eating and activity habits.3
Regular weighing can help some of us see whether our weight is stable or gradually rising. But if weighing causes distress, repeated checking, or pressure to restrict food, then it might be beneficial to use other ways to measure progress.
We can also notice whether we’re missing meals, feeling hungry more often, sleeping less, or turning to food more frequently when we’re upset. These observations can help us explain what’s been happening when we seek support.
For example, work may have got busier, and we may regularly miss lunch. By the time we get home, we’re very hungry and find ourselves eating while we prepare dinner.
In that situation, we need to work out how to make lunch possible, whether that means taking something with us, finding somewhere nearby to buy it, or discussing time for a break at work.
Similarly, if eating in the evening has become our only opportunity to relax, removing the food won’t resolve our need for rest. We may need to look at how responsibilities are shared at home or whether we can get more help.
If hunger or food noise increases after reducing medication, we should discuss this with our prescriber.
If our relationship with food is closely linked to anxiety, depression, or past trauma, we may need psychological support alongside changes to our eating habits.
Take home message
Keeping weight off is difficult because increased hunger, emotional needs, and everyday pressures can make even well-established healthy habits hard to maintain.2,3
Eating a diet based on whole foods, doing exercise we enjoy, and getting enough sleep support our health, but they won’t necessarily resolve the reasons we turn to food for comfort.
We also need to understand those reasons (why we turn to food beyond physical hunger), find other ways to manage difficult feelings, and learn from setbacks without deciding that everything we’ve been doing has failed.3
Some of us will need ongoing support from medication, even after making lasting changes to our habits. Others may maintain their weight with a lower dose or without medication.4,5,6
Long-term maintenance is possible, but we shouldn’t expect to manage every difficulty alone.
Getting help and support with persistent hunger, emotional distress, or overwhelming responsibilities can help us continue looking after our health when our usual habits become difficult to maintain.
Second Nature’s medication programme combines clinical care with registered dietitian support for eating habits, emotional eating, and weight-regain prevention, using the balanced plate approach described above.
Our study of programme records found an average weight loss of 19.1% at 12 months among active subscribers using semaglutide, with 77.7% losing at least 10%.7
Second Nature's Mounjaro and Wegovy programmes
Second Nature provides Mounjaro or Wegovy as part of our Mounjaro and Wegovy weight-loss programmes.
Why choose Second Nature over other medication providers, assuming you're eligible?
Because peace of mind matters.
We've had the privilege of working with the NHS for over eight years, helping people across the UK take meaningful steps toward a healthier, happier life.
Our programmes are designed to meet people where they are, whether that means support with weight loss through compassionate one-to-one health coaching, or access to the latest weight-loss medications (like Mounjaro and Wegovy) delivered alongside expert care from a multidisciplinary team of doctors, psychologists, dietitians, and personal trainers.
At the heart of everything we do is a simple belief: real, lasting change comes from building better habits, not relying on quick fixes. We're here to support that change every step of the way.
With over a decade of experience, thousands of lives changed, and a long-standing record of delivering programmes used by the NHS, we believe we're the UK's most trusted weight-loss programme.
We hope to offer you something invaluable: peace of mind, and the support you need to take that first step.